Improved imaging of vascular inflammation: CHAI and VISION studies

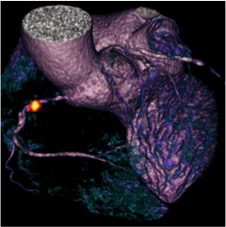
RCA imaged with DOTA

Dr James Rudd, Dr Elizabeth Warburton, Dr Anthony Davenport, and others have published two studies on the imaging of vascular inflammation.

The first study – CHAI – was funded by the British Heart Foundation and supported by the NIHR BRC: Cambridge. CHAI study is the first prospective human study to quantify hypoxia in atherosclerosis using 18F-fluoromisonidazole (FMISO) PET. Symptomatic carotid plaques were found to be more hypoxic than asymptomatic lesions, potentially identifying a novel target for drug therapy. The robust correlation between 18F-fluorodeoxyglucose (FDG) and FMISO signals suggests that hypoxia contributes to the FDG signal in FDG PET studies of atherosclerosis.

The second study – VISION – was funded by the Wellcome Trust and supported by the NIHR BRC: Cambridge. In the study, 68Ga-DOTATATE PET has been used successfully as a novel marker of atherosclerotic inflammation. Compared to FDG, 68Ga-DOTATATE offered superior coronary imaging, excellent macrophage specificity and better power to discriminate high-risk vs. low-risk lesions.

Both papers have been published in the same issue of JACC (Vascular imaging with 18F-fluorodeoxyglucose positron emission tomography is influenced by hypoxiaDetection of atherosclerotic inflammation by 68Ga-DOTATATE PET compared to 18F-FDG PET imaging). The research is hoped to open up new therapeutic avenues for atherosclerosis, the leading cause of death in the UK
and worldwide and the driver of most heart attacks and strokes.

The studies reflect the hard work of many people, cutting across disciplines within the Clinical School and beyond. For his work on the VISION study, Dr Jason Tarkin (pictured 2nd from right) was awarded the Young Investigator award from the American Heart Association in November 2016. For his efforts in the CHAI study, Dr Francis Joshi was awarded an American Heart Association Early Career Investigator Award and a British Atherosclerosis Society Binks Trust Award.

Researchers shine at Cambridge Science Festival

Researchers from the National Institute of Health Research (NIHR) Cambridge Biomedical Research Centre (BRC), took part in the Cambridge Science Festival on Sunday 26th March at the Cambridge Biomedical Campus. Hundreds of people visited the site and took a keen interest in the research happening on the campus.

As well as meeting the researchers, visitors had the opportunity to look at some of the equipment researchers use everyday, look at their current work they are doing on the campus and ask questions.

There were a wide range of displays to showcase the research and encourage children to become interested in science. With one of her real lab microscopes on display, Dr Romina Vuono talked to visitors about her Parkinson’s research, examples of her work and how the brain functions.

Teng and his team were there to talk to visitors about stroke research. Using water and ink, they had set up a circulation system to demonstrate what a healthy circulation system looks like and what we can do to maintain our own.

Crina a research associate demonstrated to children how immune cells worked by getting them to make their own bracelets. The Cambridge BRC Patient and Public Involvement team spoke to potential new members about what the panel does – reviewing research documents and working with researchers.

The Rare Diseases team talked about rare diseases and explaining how our DNA makes us all unique using the example of colouring in a large zebra.

The NIHR Cambridge BioResource were on hand to talk to people about the BioResource and how people can get involved in research, with the opportunity to sign up to the service. The team a played a game with children to understand their genetics.

From the 1st April 2017, the NIHR BRC: Cambridge began its next phase with an £114m investment from the Government to make world-first breakthroughs for the next five years, looking into 17 research themes. Professor John Bradley, Director of the NIHR Cambridge Biomedical Research Centre, said on winning the award: “We are delighted that our research excellence has been recognised by this massive investment. We look forward to continuing our work to translate Cambridge’s outstanding biomedical research into benefits for patients.”

NIHR IBD BioResource celebrates 1000th patient

The National Institute of Health Research (NIHR) Inflammatory Bowel Disease (IBD) BioResource are celebrating the recruitment of their 1,000th patient to their research programme.

Inflammatory Bowel Disease (IBD) is a term used to describe two conditions, Crohn’s disease and Ulcerative Colitis. These lifelong illnesses flare at intervals, producing debilitating symptoms including cramping abdominal pains, anaemia, weight loss and diarrhoea. They require on-going drug therapy, and many patients also require major surgery.

In the UK, more than 300,000 people are affected by IBD. The exact causes of Crohn’s disease and Ulcerative Colitis are unclear, but there is evidence that IBD can cluster in families and having an affected family member is a risk factor.

In January 2016, a new research resource was launched nationally to recruit people with IBD to help investigators better understand Crohn’s and colitis and find new treatments. The NIHR IBD BioResource sits within the NIHR BioResource – comprising volunteers from around the England who are willing to be approached to participate in research studies and trials on the basis of their genetic makeup or clinical features.

The NIHR IBD BioResource began in Cambridge just over a year ago, and the team have had a lot of interest across the country from people who want to take part. More centres are opening up for recruitment. Cambridge has recruited its 1,000th patient, and nationally 1,000 more have been recruited in the last few months alone.

The IBD BioResource recruits people diagnosed with Crohn’s disease or Ulcerative Colitis and asks them to provide a small blood sample and clinical data. Researchers then study the genetic makeup of these samples. People who sign up to the IBD BioResource are then invited back to participate in future research studies and this could involve giving another blood sample or a stool sample, completing a questionnaire or participating in a trial.

Dr Miles Parkes, a consultant gastroenterologist at Cambridge University Hospitals and national lead for the NIHR IBD BioResource project, said: “We have been delighted by the positive response to this project since we launched it in January 2016. 1,000 of our Cambridge patients with Crohn’s or colitis are now signed up to help research into these conditions – and we hope that many more from around the UK will join in the months ahead. We want to get 25,000 recruits over the next 3 years. The whole point is to have an interactive resource which allows the amazing progress in genetics seen in recent years to be translated into clinical benefit.”

Wendy Edwards, Research Manager at Crohn’s and Colitis said: “The recruitment of the first 1000 patients to the IBD Bioresource is a landmark moment and we are delighted to have part funded the project. With access to this growing resource, researchers can identify new pathways to better diagnosis and treatments for Crohn’s Disease and Ulcerative Colitis. The IBD Bioresource offers new hope to people who live with these chronic conditions on a daily basis, by opening new doors to new discoveries.”
Researchers hope more people will come forward to sign up as volunteers for the NIHR IBD BioResource, to help better understand IBD and develop new treatments for those who are living with this condition.

More information can be found at: NIHR IBD BioResource or NIHR BioResource

Crohn’s disease risk and prognosis determined by different genes, study finds


Researchers have identified a series of genetic variants that affect the severity of Crohn’s disease, an inflammatory bowel disease – but surprisingly, none of these variants appear to be related to an individual’s risk of developing the condition in the first place

Crohn’s disease is one of a number of chronic ‘complex’ diseases for which there is no single gene that causes the disease. In fact, to date around 170 common genetic variants have been identified that each increase the risk of an individual developing the disease. The conventional wisdom has been that there exists a ‘tipping point’: if someone has enough of these genes, they become very likely to develop the disease – and the more of the variants they carry, the more the severe the disease will then be.

However, in a study published today in Nature Genetics, a team of researchers led by the University of Cambridge has shown that this is not the case: genetic variants that affect the progression, or prognosis, of a disease operate independently of those that increase the likelihood of developing the disease in the first place.

“Genetic studies have been very successful at identifying genetic risk factors for Crohn’s disease, but have told us virtually nothing about why one person will get only mild disease while someone else might need surgery to treat their condition,” says Dr James Lee from the Department of Medicine at Cambridge. “We do know, though, that family members who have the disease often tend to see it progress in a similar way. This suggested to us that genetics was likely to be involved in prognosis.”

The researchers looked at the genomes – the entire genetic makeup – of more than 2,700 individuals, who were selected because they had either had experienced particularly mild or particularly aggressive Crohn’s disease. By comparing these patients’ DNA, the researchers found four genetic variants that influenced the severity of a patient’s condition. Strikingly, none of these genes have been shown to affect the risk of developing the disease.

The team then looked at all the known genetic risk variants for Crohn’s and found that none of these influenced the severity of disease. “This shows us that the genetic architecture of disease outcome is very different to that of disease risk,” adds Professor Ken Smith, Head of the Department of Medicine. “In other words, the biological pathways driving disease progression may be very different to those that initiate the disease itself. This was quite unexpected.  Past work has focussed on discovering genes underlying disease initiation, and our work suggests these may no longer be relevant by the time a patient sees the doctor. We may have to consider directing new therapies to quite different pathways in order to treat established disease”

One of the genetic variants discovered by the team was in a gene called FOXO3. This gene is involved in modulating the release of the cytokine TNFα – cytokines are proteins released into the blood by immune cells in response to infection or, in the case of conditions such as Crohn’s, to the body erroneously attacking itself. This FOXO3-TNFα pathway is also known to affect the severity of rheumatoid arthritis, another auto-inflammatory disease.

Another of the variants was close to the gene IGFBP1, which is known to play a role in the immune system. This genetic region, too, has previously been linked to rheumatoid arthritis, in a study looking at the presence of a particular antibody in patients – presence of this antibody is associated with more severe disease.

The third genetic variant was in the MHC region, which is responsible for determining how our immune cells respond to invading organisms. This region has been implicated in a number of auto-immune diseases, including Crohn’s, but the genetic variant that alters Crohn’s disease risk is different to the one that affects prognosis. The variant the team identified, which was associated with a milder course of Crohn’s disease, was shown to affect multiple genes in this region, and result in a state that is known to cause weaker immune responses.

The final variant occurred in the gene XACT, about which very little is known; however, in adults this gene appears to be mainly active in cells in the intestine – the organ affected by Crohn’s disease. “This discovery has shown us a new way of looking at disease and opens up potential new treatment options, which could substantially ease the burden of Crohn’s disease,” says Dr Lee. “What’s more, we have evidence that some of these prognosis genes will be shared with other diseases, and as such this approach could be used to improve treatment in a number of conditions.”

The study has been welcomed by Crohn’s and Colitis UK, who helped fund the study. “This is an exciting breakthrough which offers new hope for people who suffer every day from Crohn’s and Colitis,” says Dr Wendy Edwards, Research Manager at Crohn’s and Colitis UK. “The research sheds new light on why some people with inflammatory bowel disease experience more severe symptoms than others, which has been little understood until now.”

As well as its implications for Crohn’s and other diseases, the approach taken by the researchers has suggested that there is value in re-examining previous genetic studies. Around a third of the genomes of Crohn’s disease patients analysed in this study had been collected for a previous study in 2007. By dividing the patients into groups categorised by disease severity, the researchers were able ask new questions – and gain new insights – from the old data.

The research was mainly funded by NIHR Biomedical Research Centre: Cambridge, Crohn’s and Colitis UK and the Evelyn Trust.

Written by the University of Cambridge

Teaser: 
Crohn’s disease
Section: 
Home

NIHR research award for Gillian Gatiss, Addenbrooke’s liver transplant dietitian

Gillian Gatiss, a dietitian in the Addenbrooke’s team that works with patients awaiting liver transplantation, has been awarded the HEE/NIHR Clinical Doctoral Research Fellowship through the ICA HEE/NIHR Integrated Clinical Academic Programme for non-medical healthcare professions. She is set to advance knowledge through her PhD at the University of Cambridge about how the nutritional status of patients with liver cirrhosis can be improved, focusing on developing an individualised approach to their nutritional treatment.

For patients with liver disease, eating an appropriate diet is anything but straightforward. Up to 60,000 people in England and Wales have cirrhosis and numbers are rising fast. As the disease progresses, patients often experience muscle-wasting combined with either increased or decreased fat stores.

Gillian explained: “My specific job as a dietitian is to assess patients presenting for liver transplantation. I check that they are nutritionally fit and if not, we put a plan in place to improve their nutritional status before transplantation. Patients are so variable. We need better ways to help each person meet their energy requirements, eat the right food and stay as strong as possible. For example, we measure weight but the liver cirrhosis means that people are often retaining a lot of fluid and this obviously means the weight measurements can be misleading. The research award means I’ll be able to look at completely new ways to assess and respond to people’s individual needs”.

In 2011, Gillian undertook the Masters in Clinical Research, supported by NIHR through what’s now called the ICA programme. She said: “I wanted to be able to do research in practice. I was questioning how we could improve things. With the liver patients, rather than a one size fits all approach, we are looking to tailor what we do for our patients”.

Support from the Addenbrooke’s Charitable Trust (ACT) and the NIHR Biomedical Research Centre: Cambridge (BRC) was key to Gillian’s success, enabling her to develop her 2016 NIHR proposal.

The ACT/BRC Fellowship gave me the time and support I needed to develop a competitive doctoral application and it meant I could continue on a clinical/academic pathway – Gillian Gatiss

Gillian said: “After the Masters, I went back to working clinically with patients but was keen to apply for research grants. I realised the next step was to work on a PhD. But I needed support to put the HEE/NIHR Doctoral Research Fellowship application together – to review the literature, discuss the research with supervisors, develop the research protocol, consult with patients and the public, determine the training programme and finances – and I was so lucky to be one of the first recipients of the ACT/BRC internal research Fellowships. The ACT/BRC Fellowships, which are now in their third year, are intended to provide time and support for nurses, midwives and AHPs to develop competitive doctoral applications. That Fellowship enabled me to work on the NIHR proposal three days a week for six months and without it I would never have managed to pull it all together. It meant I could continue on a clinical/academic pathway. I didn’t want to leave patients behind. I wanted to carry on treating them”.

Gillian’s research will be in three parts. She explained that the first step is to rethink how patients’ energy requirements are worked out: “Dietitians use predictive equations to calculate people’s energy requirements but these simple calculations were originally designed for use across populations and not for individuals. So for this project we’ll test a new portable calorimeter – an energy calculating machine – to determine if it can give us much more precise results for each individual patient. One patient who is on our steering group said: ‘it would be fantastic to know my actual requirements”.

“The next step is to consider how appetite works in people with liver disease. We don’t know very much about how liver disease affects gut hormones, some of which stimulate appetite and some of which suppress it. But we do know that people with liver cirrhosis often have a poor appetite and they might feel full very quickly. So we’ll look at satiety after eating and levels of gut hormones in two groups – one healthy group and another group of people with liver cirrhosis – and we hope that any variations between the two groups may indicate treatments to boost appetite”.

“The final strand of our work will be to ask patients about their experiences with diet during their illness and we hope that something that we have never thought of might come up, which could be used to improve patients’ outcomes”.

I am just so delighted to see Gillian take this forward with the HEE/NIHR Fellowship.  These are nationally very competitive awards, and I want to thank the ACT and BRC for funding the internal research Fellowships that provided the time and support she needed to be successful – Professor Christi Deaton

Professor Christi Deaton, Florence Nightingale Foundation Professor of Clinical Nursing Research, said: “This research has the potential to improve nutritional assessment and management, and hopefully the outcomes of people with liver cirrhosis.  It will have implications for other patient groups as well.  I am just so delighted to see Gillian take this forward with the HEE/NIHR Fellowship.  These are nationally very competitive awards, and I want to thank the ACT and BRC for funding the internal research Fellowships that provided the time and support she needed to be successful”.

Find out more

The next round for the BRC/ACT internal research fellowships will be held in Autumn 2017.  Please contact christideatonpa@medschl.cam.ac.uk to find out more.

About the ICA HEE/NIHR Integrated Clinical Academic Programme

About Professor Christi Deaton

Funding announcement for our CRF

On Friday 18th November, the Department of Health announced a further £112 million investment into NIHR Clinical Research Facilities (CRFs) across the country.

Following a competitive application and assessment process, funding has been awarded to 23 NHS organisations. Provided over the next five years, the funding will pay for specialist research nurses and technical staff, as well as providing cutting-edge facilities to support clinical research and trials.

We can announce our NIHR/Wellcome Trust Cambridge Clinical Research Facility have had an uplift of a 6% increase in funding to £11.45 million commencing in 2017. Caroline Saunders, Director of Operations said: “We’re delighted with the funding we’ve been awarded to enable us to staff our expanding CRF, which will include four new research facilities due to open in the spring of 2017. This is excellent news for patients and healthy volunteers taking part in research and for our investigators.”

Minister for Public Health and Innovation Nicola Blackwood said: “UK researchers lead the world and our investment in this area so far has led to a variety of breakthroughs, including the first new asthma treatment in a decade, and a promising treatment for peanut allergies in children, to name just two.

“We know that such ground breaking research simply would not happen without the support of these Clinical Research Facilities. I’m delighted to announce this £112 million of extra funding to support the skilled personnel and cutting-edge facilities we need to keep the UK at the forefront of clinical research.”

Teaser: 
Funding announcement
Section: 
Home

Cocaine addiction leads to build-up of iron in brain

Cocaine addiction may affect how the body processes iron, leading to a build-up of the mineral in the brain, according to new research from the University of Cambridge. The study, published today in Translational Psychiatry, raises hopes that there may be a biomarker – a biological measure of addiction – that could be used as a target for future treatments.

Cocaine is one of the most widely-used illicit drugs in the Western world and is highly addictive. A report last year by the UK government’s Advisory Council on the Misuse of Drugs found that almost one in 10 of all 16-to 59-year-olds have used cocaine in their lifetime. Cocaine use was implicated in, but not necessarily the cause of 234 deaths in Scotland, England and Wales in 2013. However, despite significant advances in our understanding of the biology of addiction – including how the brains of people addicted to cocaine may differ in structure – there is currently no medical treatment for cocaine addiction; most individuals are treated with talking or cognitive therapies.

A team of researchers led by Dr Karen Ersche from the Department of Psychiatry at Cambridge examined brain tissue in 44 people who were addicted to cocaine and 44 healthy control volunteers. In the cocaine group, they detected excessive amounts of iron in a region of the brain known as the globus pallidus, which ordinarily acts as a ‘brake’ for inhibiting behaviour.

Particularly striking was the fact that the concentration of iron in this area was directly linked with the duration of cocaine use – in other words, the longer that participants had used cocaine, the greater the accumulation of iron. At the same time, the increased iron concentration in the brain was accompanied by mild iron deficiency in the rest of the body, suggesting that iron regulation in general is disrupted in people with cocaine addiction.

“Given the important role that iron plays in both health and disease, iron metabolism is normally tightly regulated,” explains Dr Karen Ersche from the Department of Psychiatry. “Long-term cocaine use, however, seems to disrupt this regulation, which may cause significant harm.

“Iron is used to produce red blood cells, which help store and carry oxygen in the blood. So, iron deficiency in the blood means that organs and tissues may not get as much oxygen as they need. On the other hand, we know that excessive iron in the brain is associated with cell death, which is what we frequently see in neurodegenerative diseases such as Alzheimer’s or Parkinson’s disease.”

The Cambridge researchers now aim to identify the precise mechanisms by which cocaine interacts with iron regulation. Dr Ersche believes the most likely mechanism is that cocaine disrupts iron metabolism, possibly by reducing the absorption of iron from food, increasing the permeability of the blood-brain-barrier so that more iron enters the brain, where it can accumulate.

Although excess iron in the brain is associated with neurodegeneration, there is no suggestion that cocaine addiction leads to an increased risk of Alzheimer’s or Parkinson’s disease. The mechanism underlying the increase in iron in the brain in Parkinson’s disease, for example, is different to that in cocaine addiction, as are the affected brain regions.

As an essential micronutrient, iron can only be obtained through our diet and cannot be excreted, other than through blood loss. The researchers now want to find out whether means of correcting the disruptions in iron metabolism might slow down or even reverse the accumulation of iron in the brain, and ultimately help affected individuals to successfully recover from cocaine addiction.

This work was funded by the Medical Research Council and was conducted at the NIHR Biomedical Research Centre: Cambridge and the Behavioural and Clinical Neuroscience Institute.

Written by the Unviersity of Cambridge

Teaser: 
Build up of iron on brain
Section: 
Home
Copyright © 2026 NIHR Biomedical Research Centre: Cambridge